

Published: November 2025 | Last updated: April 2026 | Editorial review and quality control: Martina N.
If you are living with HIV, hepatitis B, or hepatitis C, liver health and metabolic complications are probably never far from your mind. Antiretroviral therapy keeps HIV suppressed, but it can also contribute to weight gain, insulin resistance, and fat accumulation in the liver. Semaglutide, sold as Ozempic for type 2 diabetes and Wegovy for weight management and metabolic liver disease, is now one of the most closely watched tools for addressing exactly these problems. The research picture has moved fast in the last two years, and there is more to know than what most general health coverage gets into.
Can people with HIV or hepatitis benefit from Ozempic?
Yes, in specific ways. The 2024 SLIM LIVER trial showed semaglutide cut liver fat by an average of 31% over 24 weeks in people with HIV and metabolic dysfunction-associated steatotic liver disease (MASLD), with nearly 30% achieving complete MASLD resolution. Semaglutide is not an antiviral; it does not treat HIV, hepatitis B, or hepatitis C directly. What it does is address the fatty liver, inflammation, insulin resistance, and weight gain that often develop alongside these infections and their treatments. Always coordinate with your HIV specialist or hepatologist before starting.
Key Takeaways
- In the SLIM LIVER trial, semaglutide reduced liver fat by 31% on average and produced complete MASLD resolution in 29% of HIV-positive participants over 24 weeks.
- Wegovy received accelerated FDA approval in August 2025 for treating MASH with stage 2 to 3 liver fibrosis, the second drug ever approved for this condition.
What Ozempic Is and How It Works in the Body
Ozempic is the brand name for semaglutide, a drug that mimics GLP-1 (glucagon-like peptide-1), a hormone the body naturally produces in response to eating. When GLP-1 binds to its receptors in the pancreas, stomach, brain, and other tissues, it slows digestion, signals the brain to reduce appetite, and tells the pancreas to release insulin more efficiently in response to blood sugar. The result is better glucose control, reduced caloric intake, and meaningful weight loss in most people over time.
That mechanism sounds straightforward for diabetes management. What makes semaglutide interesting beyond its approved uses is where else GLP-1 receptors live. The liver, immune cells, and vascular tissue all carry these receptors, which means semaglutide's reach extends well beyond glucose regulation. For people whose infections (HIV, hepatitis B, hepatitis C) drive metabolic disruption and chronic low-grade inflammation, that extended reach matters.
Semaglutide is currently FDA-approved under the Ozempic brand for type 2 diabetes and under the Wegovy brand for obesity. In August 2025, Wegovy received accelerated FDA approval for a third indication: treating metabolic dysfunction-associated steatohepatitis (MASH) with moderate to advanced liver fibrosis. That regulatory milestone is significant for anyone with a liver condition. It means the drug now has formal recognition as a liver disease treatment, not just a metabolic drug that happens to help the liver.
| Brand Name | Approved Use | Notes |
|---|---|---|
| Ozempic | Type 2 diabetes | Weekly subcutaneous injection; also used off-label for weight loss |
| Wegovy | Obesity / weight management | Higher dose formulation than Ozempic |
| Wegovy | MASH with stage 2 to 3 fibrosis | Accelerated FDA approval granted August 2025 |
Why People with HIV Face Higher Liver and Metabolic Risk
Here is something that often gets lost in the general conversation about HIV: getting on antiretroviral therapy and becoming undetectable does not mean metabolic risk disappears. For a significant number of people on modern ART, especially regimens containing integrase strand transfer inhibitors (INSTIs), weight gain is a real side effect. That weight gain, combined with the metabolic disruption the virus itself causes, creates fertile ground for fatty liver disease, insulin resistance, and cardiovascular disease.
Picture being two years into a successful HIV treatment regimen, viral load undetectable, CD4 count strong, by most measures doing great, and then your doctor starts flagging elevated liver enzymes and rising triglycerides. That is not uncommon. According to the National Institutes of Health, an estimated 30 to 40 percent of people living with HIV have metabolic dysfunction-associated steatotic liver disease (MASLD), the condition formerly known as non-alcoholic fatty liver disease. That rate is somewhat higher than in the general population, and crucially, HIV-positive people appear to experience more rapid disease progression when MASLD is present.
The reasons are layered. Chronic HIV infection drives persistent immune activation even when the virus is suppressed. The immune system stays in a low-grade alert state, and that sustained inflammation takes a toll on the liver and cardiovascular system over time. Add in the metabolic effects of long-term ART, and the risk profile for liver disease, type 2 diabetes, and heart disease climbs in ways that do not apply to the general population in the same way.
People with hepatitis B and hepatitis C face a different but overlapping challenge. Both viruses directly target the liver, causing chronic inflammation that can progress over years to fibrosis, cirrhosis, and liver cancer if untreated. Even with effective antiviral treatment for hepatitis C and suppressive therapy for hepatitis B, the metabolic aftermath of years of viral inflammation can persist. Co-infection (having HIV plus hepatitis B or C simultaneously) amplifies all of these risks further.
This article is published by stdrapidtestkits.com, which sells at-home STI testing kits including HIV and hepatitis tests. We recommend products based on fit-for-purpose for the reader's concern, not commercial benefit.
What the SLIM LIVER Study Found, and Why It Matters
The most rigorous evidence for semaglutide in HIV to date comes from the SLIM LIVER study (ACTG A5371), a Phase IIb clinical trial funded by the National Institute of Allergy and Infectious Diseases and conducted across sites in the United States and Brazil. It is the first clinical trial specifically designed to test semaglutide for MASLD in people living with HIV. The results, published in the Annals of Internal Medicine and presented at CROI 2024, are genuinely striking.
Fifty-one adults with HIV on suppressive antiretroviral therapy were enrolled (49 of whom were included in the per-protocol analysis). All had confirmed MASLD (at least 5 percent liver fat content by MRI) plus cardiovascular risk factors such as a large waist circumference, insulin resistance, or pre-diabetes. Participants self-administered subcutaneous injections of semaglutide once weekly for 24 weeks, ramping up to a 1 mg dose. At the end of six months, liver fat content was measured again using the same MRI-based method.
According to the NIH, participants experienced an average 31 percent reduction in liver fat. Twenty-nine percent achieved complete MASLD resolution, meaning their liver fat dropped to 5 percent or less of total liver content. Nearly 60 percent saw at least a 30 percent relative reduction, the threshold associated with meaningful histological improvement. Average weight loss was 7.8 kg (about 17 lbs) over the six-month period. Fasting blood glucose and triglyceride levels also improved significantly.
What makes these results particularly notable is not just the liver fat reduction. It is that they appear to mirror or exceed what semaglutide achieved in HIV-negative people in earlier studies, even at a lower dose. As the investigators noted, people with HIV achieved similar liver fat reductions with just 1 mg weekly that HIV-negative participants required higher doses to match over a longer timeframe. Nobody knows exactly why yet, but the clinical implication is that people with HIV may be especially responsive to this drug's liver effects.
One important caveat: SLIM LIVER was a small pilot study without a placebo control arm. That means a confounding factor cannot be fully ruled out, and larger randomized trials are still needed. The investigators acknowledged this directly, but also noted the primary effect size was large enough to support a genuine drug benefit.
A weekly injection of semaglutide was safe and reduced the amount of fat in the liver by 31% in people with HIV.
Inflammation, Immune Activation, and Cardiovascular Risk
The liver fat story is compelling enough on its own, but the follow-up data goes further, and it is the part most relevant for long-term health outcomes in people with HIV.
A secondary analysis from SLIM LIVER, presented at the AASLD Liver Meeting in November 2025, looked at cardiovascular biomarkers in participants who lost at least five pounds during the study. The findings showed semaglutide was associated with favorable changes in a wide range of cardiovascular risk markers including lipoproteins, glycoproteins, and inflammatory cytokines. Importantly, many of these improvements appeared independent of weight loss, liver fat reduction, and insulin resistance changes. That suggests semaglutide may have direct anti-inflammatory effects on the cardiovascular system in people with HIV, beyond metabolic effects that trickle downstream.
Separately, an analysis of 108 non-diabetic HIV-positive adults on ART, also reported by aidsmap and presented around CROI 2024, measured specific inflammation markers at baseline and at 32 weeks. There were significant reductions in high-sensitivity C-reactive protein (approximately 40 percent), interleukin-6 (approximately 19 percent), and soluble CD163, a marker of macrophage activation (approximately 12 percent). All three markers are elevated in people with HIV even on suppressive therapy, and all three are independently associated with cardiovascular disease risk. Those reductions are notable precisely because they are not explained by weight loss alone. (This 108-person cohort is a separate analysis from the 51-person SLIM LIVER trial discussed above.)
Beyond the cardiovascular angle, 2025 CROI analyses of SLIM LIVER participants suggested additional potential benefits: signs of slower epigenetic aging, improved cognitive function markers, a healthier gut microbiome composition, and reduced alcohol use. These are early, exploratory findings, not conclusions, but they reinforce how broadly GLP-1 receptor agonists may act in the biology of people living with HIV.
Cardiovascular disease is one of the leading causes of death among people with HIV today. The combination of persistent immune activation, metabolic disruption from ART, and traditional risk factors creates a cardiovascular burden that antiretrovirals alone do not fully address. If semaglutide can reliably and meaningfully reduce that burden through its effects on liver fat, visceral adipose tissue, and inflammation, that is a potentially significant contribution to healthy aging with HIV.
| Outcome Measure | Result at 24–32 Weeks |
|---|---|
| Average reduction in liver fat content | 31% relative decrease |
| Complete MASLD resolution | 29% of participants |
| At least 30% relative liver fat reduction | 58% of participants |
| Average weight loss | 7.8 kg (about 17 lbs) |
| High-sensitivity C-reactive protein (hsCRP, separate 108-person cohort) | About 40% decrease |
| Interleukin-6 (IL-6, separate 108-person cohort) | About 19% decrease |
| Soluble CD163 (separate 108-person cohort) | About 12% decrease |
| Tolerability | All 49 SLIM LIVER per-protocol participants completed the full 24 weeks |
Semaglutide and Liver Disease in Hepatitis B and Hepatitis C
The SLIM LIVER trial focused on HIV specifically, but the broader story of semaglutide and liver disease is directly relevant to people with hepatitis B and hepatitis C. Both infections cause chronic liver inflammation, and one of the most common downstream complications for people with chronic hepatitis is exactly the kind of metabolic liver disease that semaglutide has been shown to address.
The landmark evidence here comes from the Phase 3 ESSENCE trial, published in the New England Journal of Medicine in April 2025. This large-scale trial enrolled around 1,200 patients with biopsy-confirmed MASH and moderate to advanced liver fibrosis (stages 2 to 3) and randomized them to receive semaglutide 2.4 mg weekly or placebo for up to 240 weeks. The 72-week interim analysis showed a substantially higher rate of resolution of steatohepatitis without worsening of fibrosis in the semaglutide group than in the placebo group, along with a higher rate of fibrosis improvement and meaningful weight loss. These results led directly to the FDA's accelerated approval of Wegovy for MASH in August 2025, making it only the second-ever FDA-approved treatment for this condition.
That approval applies to people with MASH regardless of what caused the underlying liver inflammation. For someone with chronic hepatitis B who has developed concurrent fatty liver disease over years, or a person who cleared hepatitis C but whose liver still carries metabolic damage, the relevance is clear. Semaglutide is not treating the virus itself; it is addressing the metabolic and inflammatory environment the liver has been left in.
There are limits to keep in mind. The ESSENCE trial did not enroll people specifically because of hepatitis B or C; it targeted MASH with fibrosis broadly. And in a separate study, semaglutide did not show significant improvement in liver fibrosis for people with NASH-related cirrhosis (stage 4 fibrosis), suggesting the drug works better at earlier stages. The 2025 AASLD practice guidance specifically recommends semaglutide for patients with stage 2 to 3 fibrosis, not for those who have progressed to cirrhosis.
For people with chronic hepatitis B or C on effective antiviral therapy who want to know whether semaglutide might benefit their liver health, this conversation belongs with their hepatologist. The science is genuinely promising, but it is nuanced, and where someone sits on the spectrum of liver disease matters considerably.

Drug Interactions: What to Discuss With Your HIV Pharmacist
People with HIV often take multiple daily medications including ART, sometimes hepatitis antivirals, sometimes supplements for liver support. So when a new drug like semaglutide enters the picture, the first practical question is interactions.
Semaglutide is metabolized through proteolysis, not through the cytochrome P450 enzyme pathway (CYP3A4) that handles many ART drugs. That means it largely bypasses the classic drug-drug interaction route relevant to boosted protease inhibitors and other CYP-handled antiretrovirals. So far, no major interactions have been reported with common HIV regimens including integrase inhibitors like dolutegravir.
The interaction worth flagging is mechanical rather than metabolic. Semaglutide slows gastric emptying, which could theoretically affect the absorption timing of oral antiretrovirals. The FDA's prescribing information describes this effect as generally not clinically significant, but the specific combination of semaglutide with complex HIV regimens has not been extensively studied. For people on hepatitis C direct-acting antivirals (such as sofosbuvir/velpatasvir) who experience nausea or slowed digestion early in semaglutide titration, dose-timing discussions with a pharmacist are sensible. People with cirrhosis or advanced fibrosis may also have altered tolerability and should be monitored more closely.
The practical move: loop in your HIV specialist or HIV pharmacist before starting. Some HIV clinics are already integrating GLP-1 agonists into metabolic care plans, and your provider will know whether your specific regimen warrants extra monitoring.
How to Test at Home for HIV and Hepatitis B or C
Whether you are newly diagnosed, managing ongoing treatment, or just staying on top of your sexual health, knowing your status for HIV and hepatitis is the foundation of everything else. You cannot optimize treatment you do not know you need. For many people, especially those navigating busy schedules or privacy concerns, routine clinic visits do not always happen on the ideal timeline. That is where at-home rapid testing closes a real gap.
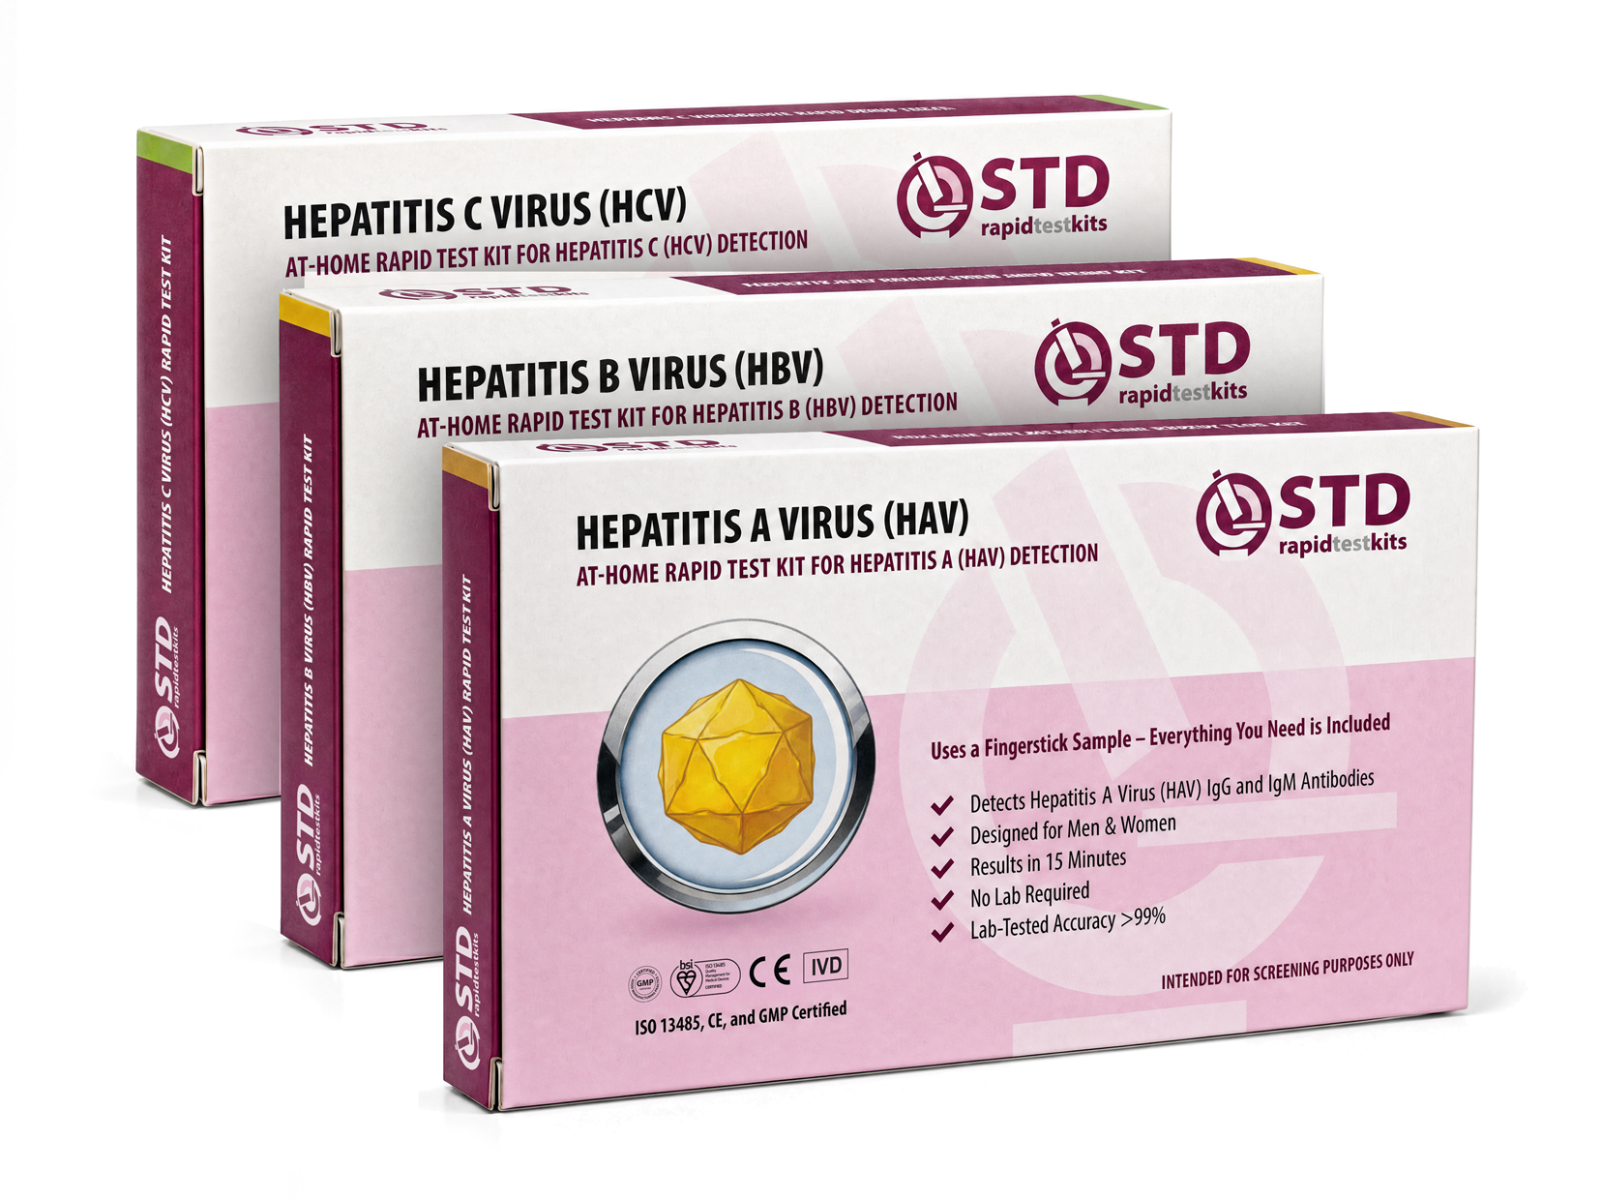
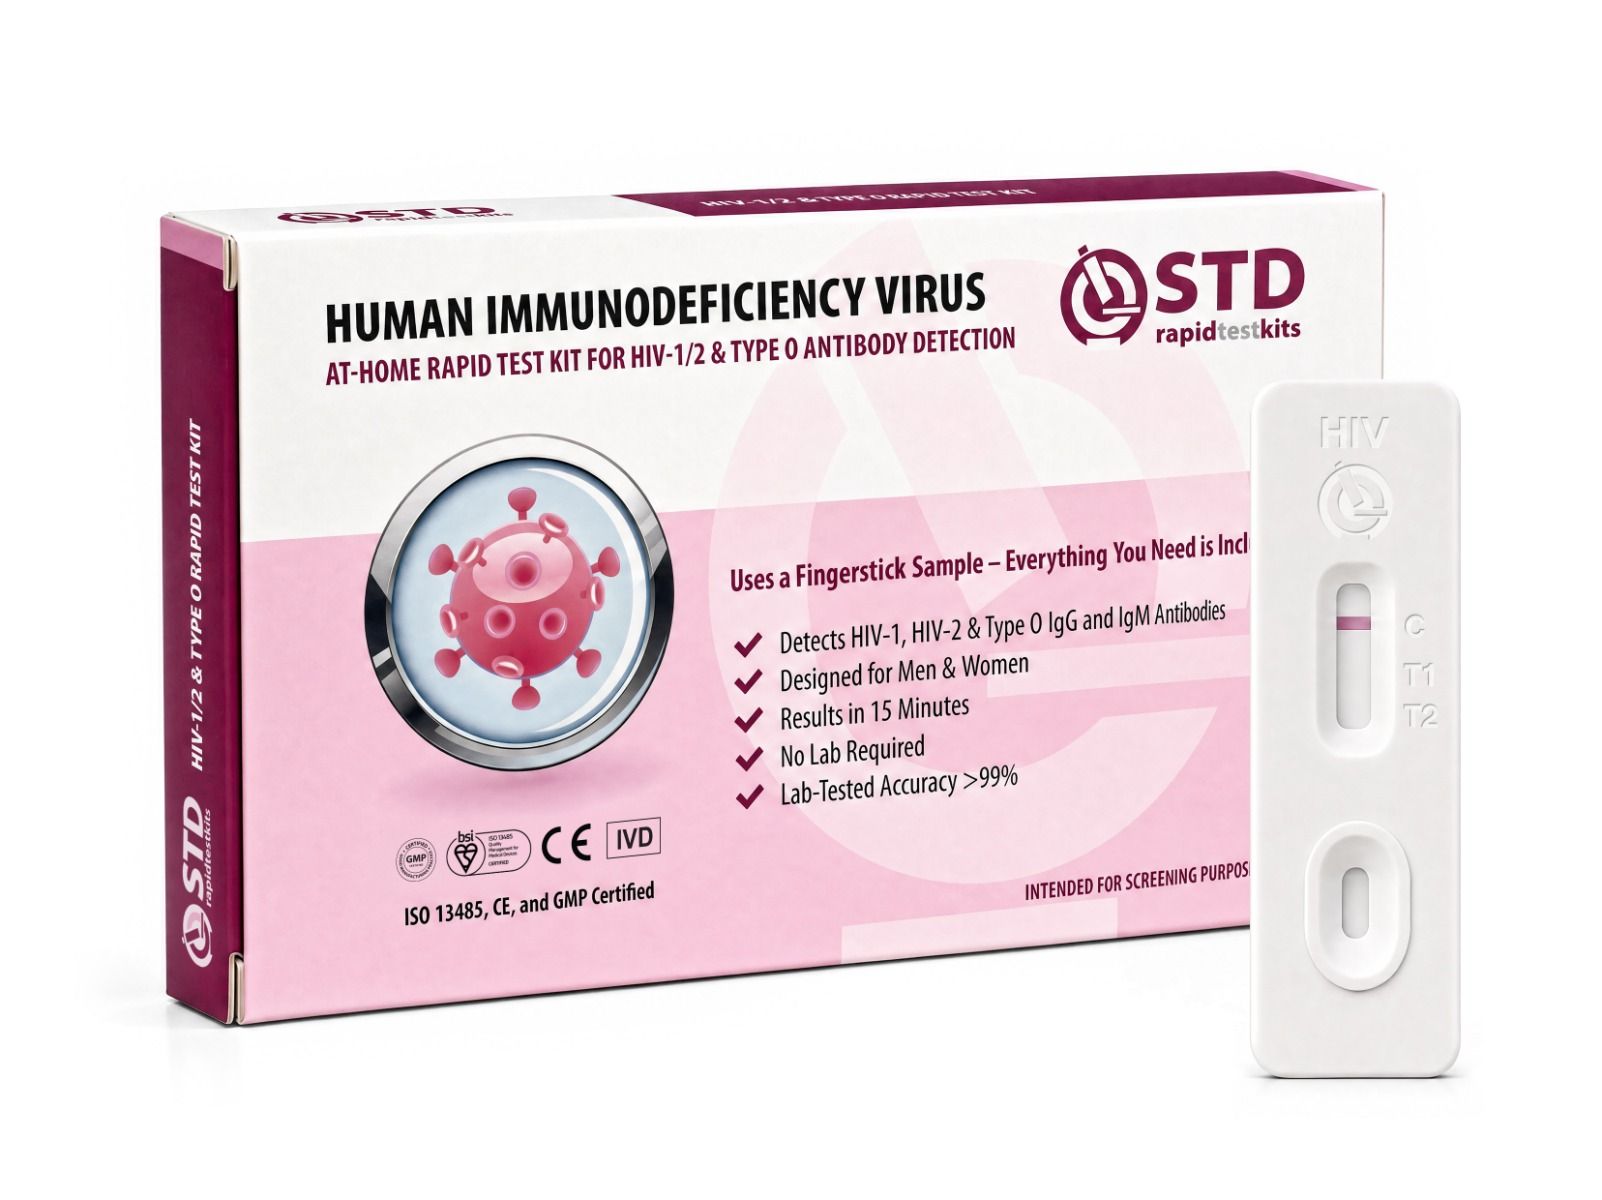
At-home rapid test kits for HIV, hepatitis B, and hepatitis C work exactly as the name suggests: a small fingerstick blood sample, a lateral flow device, and a result in about 15 to 20 minutes. No lab, no clinic, no waiting. The HIV 1&2 At-Home Rapid Test Kit and the Hepatitis B & C 2-in-1 At-Home Rapid Test Kit allow you to screen for these infections from home, discreetly, on your own schedule.
Testing windows matter, and getting them right affects how much you can trust a result. For HIV, testing from 6 weeks after potential exposure gives a reliable first indicator, and retesting at 12 weeks gives near-certainty. For hepatitis B, test from 6 weeks after exposure. For hepatitis C, the window is a bit longer: test from 8 to 11 weeks after potential exposure for an accurate result. Testing before these windows risks a false negative. The body simply has not produced enough detectable markers yet, with no reflection on test quality.
A positive at-home result is not a final diagnosis. It is a signal to see a healthcare provider for confirmatory testing and to discuss next steps. A negative result after the appropriate window period is genuinely reassuring, and getting there does not have to mean a clinic visit. For people living with HIV or hepatitis who want to monitor between clinic appointments, or for anyone who has had potential exposure and wants answers fast, at-home testing is one of the most practical tools available.
| Infection | Earliest reliable test window | Confirmation / retest |
|---|---|---|
| HIV | 6 weeks after exposure | Retest at 12 weeks for near-certainty |
| Hepatitis B | 6 weeks after exposure | Confirm any positive with a healthcare provider |
| Hepatitis C | 8 to 11 weeks after exposure | Confirm any positive with a healthcare provider |
What Regular Monitoring Looks Like on Semaglutide
If you are living with HIV or hepatitis and considering semaglutide with your doctor, there is a specific set of markers worth tracking, and this monitoring looks different from what a person without these infections would need.
Viral load is always the first priority. For HIV, standard practice involves regular viral load testing after any regimen change to confirm continued suppression, with checks typically recommended at 4 to 12 weeks following a switch and then at established intervals when stable. Semaglutide is not an antiretroviral; it does not affect HIV viral load directly, but your overall treatment picture matters. Any new medication should be added with your HIV specialist's knowledge. For hepatitis B, viral load testing quantifies how much HBV DNA is circulating in the blood, which informs both transmission risk and disease activity. For hepatitis C, viral load assessment measures treatment response and confirms whether cure has been achieved after direct-acting antiviral therapy.
Beyond viral load, metabolic markers need attention. The SLIM LIVER investigators tracked fasting blood glucose, triglycerides, liver enzymes (ALT and AST), and waist circumference as their primary metabolic endpoints. These make sense for anyone managing HIV-associated metabolic syndrome. People with hepatitis B or C should also have regular liver function tests, and their hepatologist may use additional non-invasive tools like FibroScan or the ELF score to track liver stiffness and fibrosis over time. The 2025 AASLD guidance recommends assessing treatment response at 72 weeks using these non-invasive markers, looking for meaningful improvements in ALT and liver stiffness measurements as indicators of MASH resolution.
If you are someone who goes weeks or months between clinic visits, whether by circumstance or by choice, at-home testing for HIV and hepatitis can help bridge the monitoring gap. At-home rapid kits do not replace comprehensive bloodwork; they are not measuring viral load, for instance. But they can confirm active antibody presence and serve as a useful checkpoint. Paired with regular clinical monitoring, they help you stay oriented to your health status in real time.
Important Limitations and Conversations to Have
Semaglutide is generating real excitement in HIV and hepatology circles, and the data justifies that. But there are important caveats that belong in any honest conversation about this drug for people with HIV and hepatitis.
First, semaglutide is not an antiviral. It does not treat HIV, hepatitis B, or hepatitis C. It does not suppress viral replication or reduce viral load. What it does is address the metabolic and hepatic complications that arise from these infections and their treatments. If antiretroviral therapy or hepatitis treatment is not well-managed, semaglutide is not a substitute for that foundation.
Second, on drug interactions: see the dedicated section above. The short version is that semaglutide largely bypasses the CYP3A4 pathway most ART drugs share, but the gastric-emptying effect on oral-medication absorption timing has not been studied across every HIV regimen, so coordinate with your HIV specialist before starting.
Third, if liver disease has already progressed to cirrhosis (stage 4 fibrosis), the evidence does not currently support semaglutide for improving fibrosis at that stage. The AASLD guidelines are specific: the best candidates for semaglutide for MASH are people with stage 2 to 3 fibrosis, not those who have progressed further. Someone with compensated cirrhosis already on semaglutide for another approved indication should be monitored carefully, but using semaglutide specifically to reverse cirrhosis is not supported by the current evidence base.
Fourth, the most common adverse effects are gastrointestinal: nausea, diarrhea, vomiting, and abdominal discomfort. They are more frequent in the early weeks of treatment as the dose is being titrated upward. In the SLIM LIVER trial, these were mostly grade 1 in severity, and all 49 per-protocol participants completed the full treatment course. That tolerability is encouraging, but it still means the first few weeks often involve some adjustment. Hypoglycemia is rare unless semaglutide is combined with insulin or sulfonylureas, which is uncommon for people not also being treated for type 2 diabetes.
Finally, long-term safety in HIV-positive populations specifically is still being studied. SLIM LIVER ran 24 weeks. Real-world cohorts are now being assembled, and several follow-on trials are in planning stages. For now, current use is reasonable in coordination with specialists, with the caveat that the evidence base will continue to evolve.
If your doctor has not brought up semaglutide and you think it might fit your situation, prepare a focused ask. Bring recent labs (ALT, AST, triglycerides, fasting glucose, weight history). Use the clinical terms ("MASLD," "HIV-associated metabolic syndrome," "post-DAA fibrosis") that frame the question in terms your provider works with. Reference the SLIM LIVER and ESSENCE trials by name. Ask directly: "Could semaglutide help manage my fatty liver or metabolic markers, even though I am not diabetic?" If your primary provider is unfamiliar, an HIV pharmacist, infectious disease nurse, or hepatologist may be a better starting point.
FAQs
- Can people with HIV take Ozempic?
- Yes, and the evidence is encouraging. The SLIM LIVER trial enrolled people with HIV and found semaglutide reduced liver fat by 31% on average over six months, with all 49 per-protocol participants completing the full treatment course. HIV specialists should be involved in any decision to start semaglutide given the complexity of antiretroviral regimens and the need for coordinated monitoring.
- Does Ozempic treat hepatitis B or hepatitis C directly?
- No. Semaglutide has no antiviral activity against hepatitis B or C. What it does is address the metabolic and liver complications (fatty liver, inflammation, insulin resistance) that frequently develop alongside or after these infections. For treating the actual viruses, antiviral medications prescribed by a specialist remain the standard of care.
- How much does semaglutide reduce liver fat in HIV patients?
- In the SLIM LIVER Phase IIb trial, participants with HIV and MASLD saw an average 31 percent relative reduction in liver fat over 24 weeks on semaglutide 1 mg weekly. Nearly 30 percent achieved complete resolution of MASLD, and almost 60 percent met the threshold for clinically meaningful liver fat reduction.
- What is MASLD and why does it matter for people with HIV?
- MASLD (metabolic dysfunction-associated steatotic liver disease) is the new name for non-alcoholic fatty liver disease, essentially excess fat accumulation in the liver not caused by alcohol or viral hepatitis. Between 30 and 40 percent of people with HIV develop MASLD, somewhat higher than the general population rate, and they tend to progress through the stages of liver disease faster. Left unaddressed, MASLD can lead to MASH, fibrosis, cirrhosis, and liver cancer.
- Can semaglutide help with weight gain caused by HIV medications?
- Yes, this is one of the more practical applications for people with HIV. Integrase strand transfer inhibitors, now the most commonly used antiretroviral class, are associated with weight gain in some patients. Semaglutide produced average weight loss of 7.8 kg in SLIM LIVER participants and separately led to roughly 6 percent body weight reduction over one year in a broader cohort of HIV-positive people in real-world data.
- Is Ozempic FDA-approved for liver disease?
- Yes, but specifically for MASH with moderate to advanced fibrosis (stages 2 to 3). The Wegovy formulation received accelerated FDA approval for this indication in August 2025, based on interim results from the Phase 3 ESSENCE trial. Ozempic itself remains approved for type 2 diabetes only; the liver disease approval applies to the higher Wegovy dose.
- Does semaglutide interact with antiretroviral drugs?
- There is a theoretical interaction risk because semaglutide slows gastric emptying, which could affect how some oral antiretrovirals are absorbed. The FDA considers this effect generally not clinically significant, but it has not been thoroughly studied across all HIV regimen types. Anyone on ART considering semaglutide should discuss their specific medications with their HIV specialist before starting. Semaglutide is not metabolized through CYP3A4, so the classic drug-drug interaction pathway is largely bypassed.
- How do I test for HIV and hepatitis B or C at home?
- At-home rapid test kits use a fingerstick blood sample and a lateral flow device, with a result in about 15 to 20 minutes. For HIV, test from 6 weeks after potential exposure for a first result and retest at 12 weeks for certainty. For hepatitis B, test from 6 weeks. For hepatitis C, test between 8 and 11 weeks after exposure. A positive at-home result should always be confirmed by a healthcare provider.
- What is the testing window for HIV after potential exposure?
- Test at 6 weeks after potential exposure for an initial indicator; this catches the majority of true infections. Retest at 12 weeks for near-certainty. Testing in the first two weeks is unlikely to be accurate because the body has not yet produced detectable levels of HIV antibodies. Fourth-generation lab tests (antigen plus antibody) close that early window faster than antibody-only rapid tests, so very recent high-risk exposures are best worked up at a clinic in addition to home screening.

- U.S. National Institutes of Health (NIAID). News release on the SLIM LIVER (ACTG A5371) trial: semaglutide reduces severity of common liver disease in people with HIV.
- Annals of Internal Medicine. Open-label semaglutide reduces MASLD in people with HIV: SLIM LIVER (ACTG A5371) primary results paper.
- New England Journal of Medicine. ESSENCE trial: Phase 3 trial of semaglutide in metabolic dysfunction-associated steatohepatitis (MASH) with stage 2 to 3 fibrosis, published April 2025.
- Aidsmap. Semaglutide improves fatty liver disease and inflammation markers in people with HIV.
- American Association for the Study of Liver Diseases (AASLD). 2025 practice guidance covering semaglutide use in patients with MASH and stage 2 to 3 fibrosis.
- U.S. Centers for Disease Control and Prevention. HIV testing window periods and recommended retest intervals.
- U.S. Centers for Disease Control and Prevention. Viral hepatitis testing recommendations for hepatitis B and hepatitis C.
