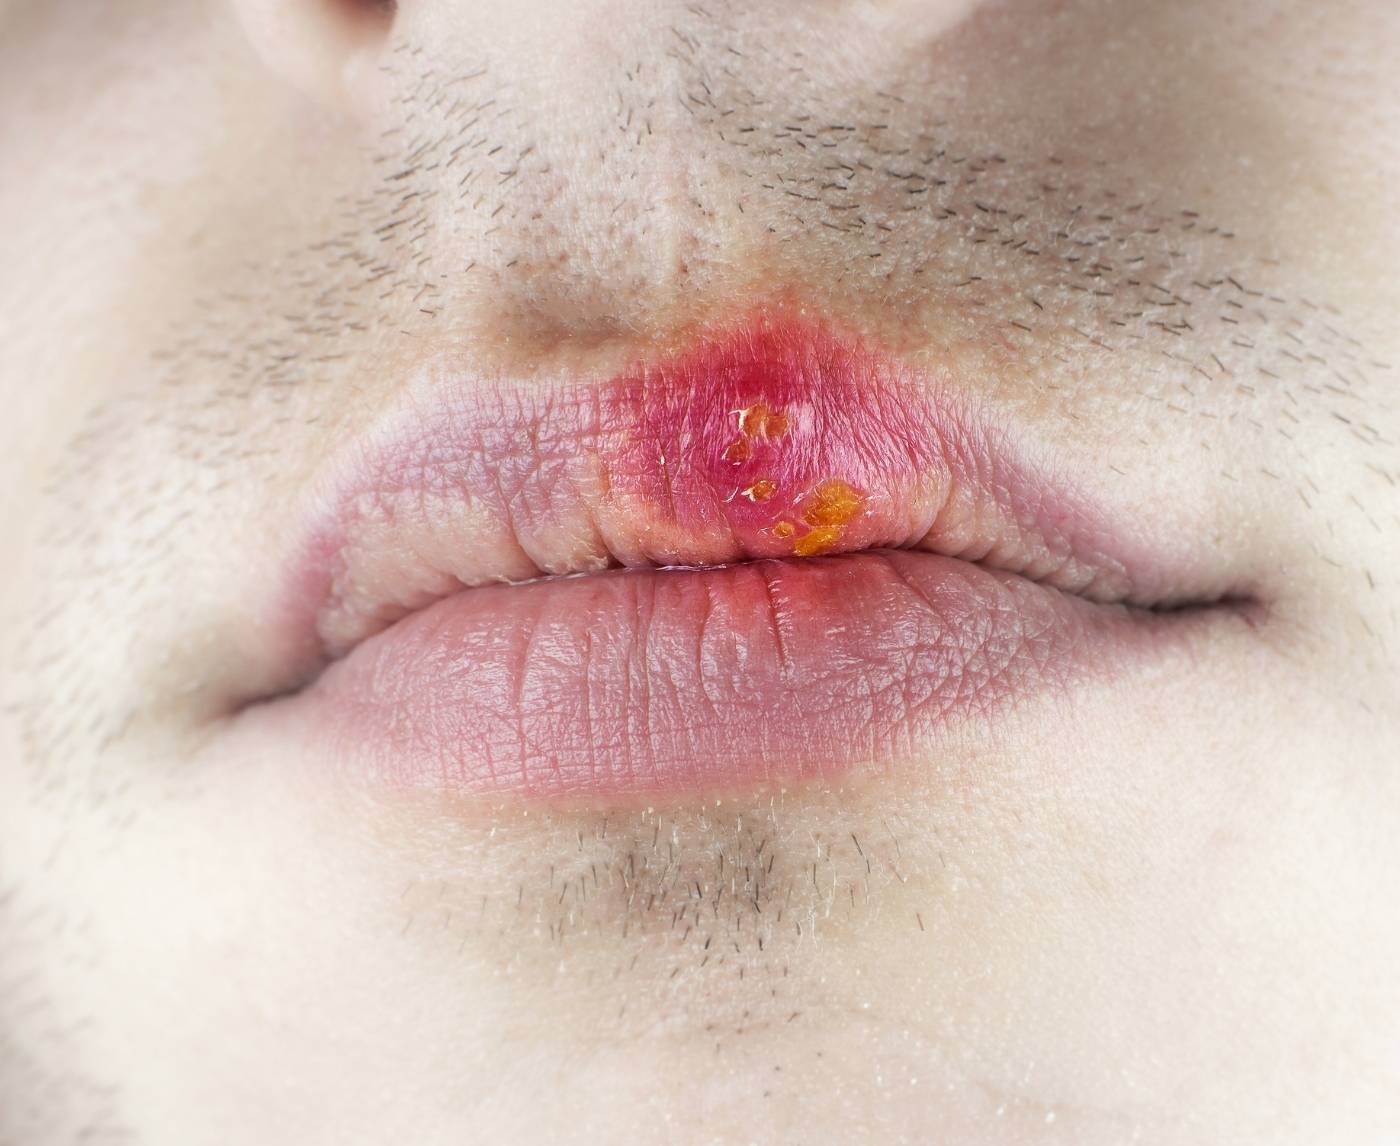
Published: November 2025 | Last updated: May 2026 | Editorial review and quality control: Martina N.
What is the difference between HSV-1 and HSV-2?
HSV-1 most often causes oral herpes (cold sores); HSV-2 most often causes genital herpes. They spread differently, but either can infect either site, so where an outbreak appears does not always confirm the strain. A type-specific blood antibody test taken at least 12 weeks after exposure is the clearest way to distinguish them when no sore is present.
Most people who carry HSV-1 or HSV-2 have never been told they do. The two viruses share a name and most of their basic biology, yet they spread differently, recur differently, and feel different for the people living with them. This guide covers what each one does, how transmission actually works, what at-home and clinic testing can and cannot tell you, and which common beliefs about herpes are simply wrong.
A note on the publisher: stdrapidtestkits.com sells at-home STI testing kits, and we recommend a product only when it fits the reader's concern. The herpes kits we sell are fingerstick blood antibody tests, useful at the right time after exposure and explained plainly below. For an active sore or lesion, the right tool is a clinician-administered swab PCR, which we do not sell; we flag that distinction wherever it matters.
Key Takeaways
- HSV-1 and HSV-2 are different viruses with different transmission patterns, but either can infect the mouth or the genitals depending on how exposure happened.
- A type-specific blood antibody test 12 or more weeks after exposure can identify HSV-1, HSV-2, or both, even if you have never had a visible outbreak; a positive screening result is best confirmed by a clinician's lab test.
How HSV-1 and HSV-2 differ
HSV-1 and HSV-2 are members of the human herpesvirus family. Their genomes are roughly 50 percent similar, and they share most of the same machinery for entering cells, replicating, and establishing lifelong latency in nerve tissue. What separates them is which nerve cluster each virus settles into once it gets there.
HSV-1 typically establishes latency in the trigeminal ganglion, the nerve cluster behind the cheekbone that supplies sensation to the face. That is why HSV-1 outbreaks usually appear on or around the lips. HSV-2 typically settles into the sacral ganglia at the base of the spine, which is why HSV-2 outbreaks appear in the genital and anal area.
That residency preference is a tendency rather than a strict rule. If HSV-1 reaches the genital area through oral sex, it can establish itself in the sacral ganglia and cause genital herpes. The reverse happens too: HSV-2 transmitted to the mouth can cause oral lesions, though this is less common. Once the virus has chosen a residency site, future outbreaks emerge from that same site.
A few differences are clinically meaningful for someone trying to understand their own situation:
- Genital HSV-1 tends to recur far less often than genital HSV-2. The CDC STI Treatment Guidelines describe recurrences as much more frequent for HSV-2 than for HSV-1, particularly in the first few years after infection.
- HSV-2 sheds asymptomatically more often than HSV-1, so HSV-2-positive people can transmit the virus on more days when they have no visible symptoms.
- HSV-1 has been rising as a cause of first-episode genital herpes in younger adults, especially in higher-income countries where childhood oral HSV-1 infection is becoming less common.
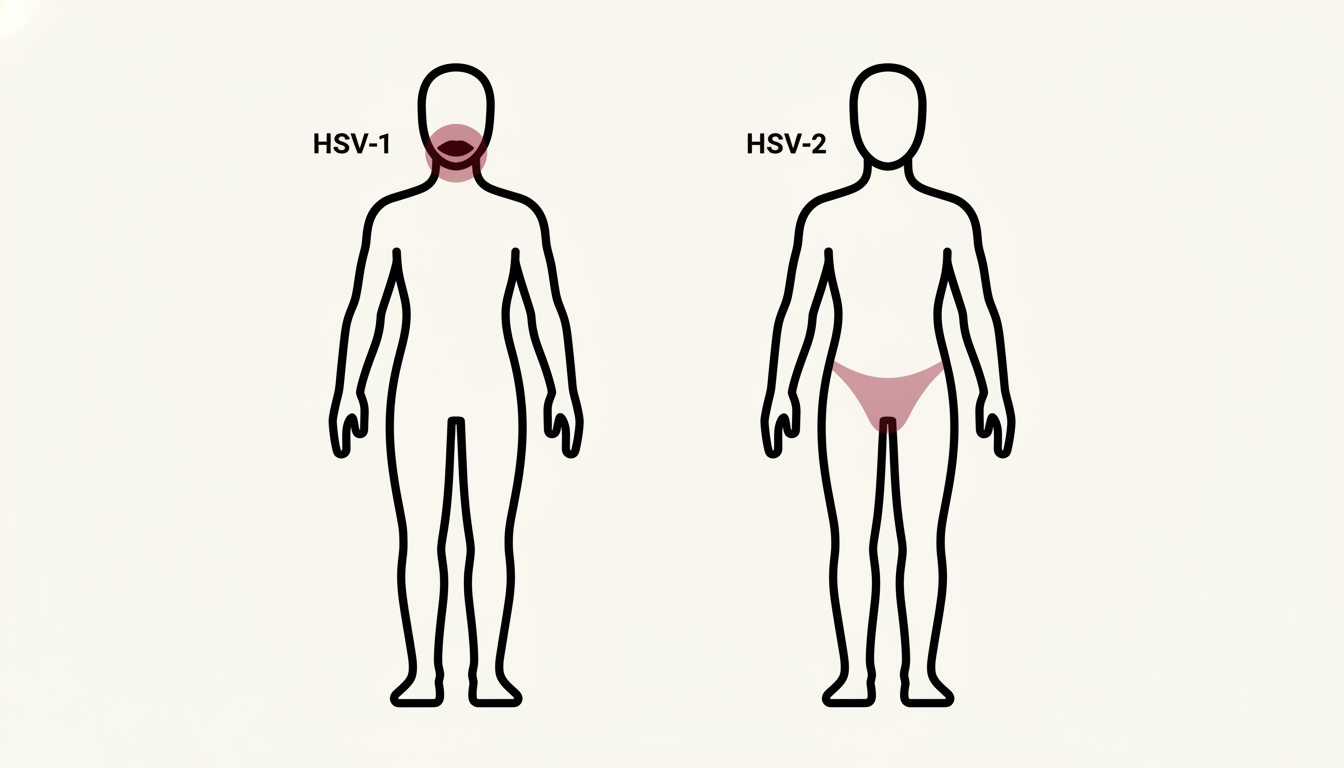
HSV-1 vs HSV-2 at a glance
The table below summarizes how the two viruses compare on the points readers ask about most: where outbreaks appear, how each spreads, how common they are worldwide, and what each means in pregnancy. The global prevalence figures come from the World Health Organization.
HSV-1 vs HSV-2
| Attribute | HSV-1 | HSV-2 |
|---|---|---|
| Most common outbreak site | Lips, mouth, face | Genitals, anal area, thighs |
| Typical transmission route | Saliva, skin contact, oral sex | Vaginal, anal, oral sex |
| Global prevalence (WHO) | About 3.8 billion people under 50 (about 64%) | About 520 million aged 15 to 49 (about 13%) |
| Genital recurrence rate | Less frequent | More frequent, especially the first few years |
| Asymptomatic shedding | Lower | Higher |
| Pregnancy concern | Lower neonatal risk | Higher neonatal risk, especially a primary third-trimester infection |
Either virus can infect either site, so the strain is confirmed by testing, not by where an outbreak appears.
Recognizing herpes symptoms
When symptoms do appear, the pattern is similar for both strains. The classic course of an outbreak runs through four phases:
- Prodrome. Tingling, itching, or burning in the area where the outbreak will appear, usually 12 to 48 hours before any visible lesion.
- Vesicle. Small fluid-filled blisters in clusters, typically 2 to 10 mm across.
- Ulcer. Blisters break and form shallow open sores that can be painful.
- Crust and heal. Sores crust over and heal. First outbreaks heal in 7 to 14 days; recurrences in 5 to 10 days.
First outbreaks are usually the most severe. They can include systemic symptoms: fever, body aches, swollen lymph nodes, headache, and general malaise. Many people describe the first episode as feeling like the flu with painful sores added on top. Recurrent outbreaks are typically milder, more localized, and shorter.
A large share of people infected with either HSV-1 or HSV-2 never have a recognized outbreak. The CDC's herpes information page notes that most people with genital herpes have no symptoms, or symptoms so mild they go unnoticed or are mistaken for a pimple or ingrown hair. Symptoms can also be confused with jock itch, a yeast infection, a urinary tract infection, or a hemorrhoid. That is one reason herpes is so widespread: most transmissions happen without anyone realizing they were infectious.
If your concern is specifically a sore around the mouth, the differential diagnosis includes canker sores (which sit inside the mouth on soft tissue, unlike cold sores, which sit on the lip border), angular cheilitis, impetigo, and contact dermatitis. A clinical exam during an active sore is the most reliable way to confirm a herpes lesion, and PCR swab testing of the sore at a clinic remains the laboratory gold standard.
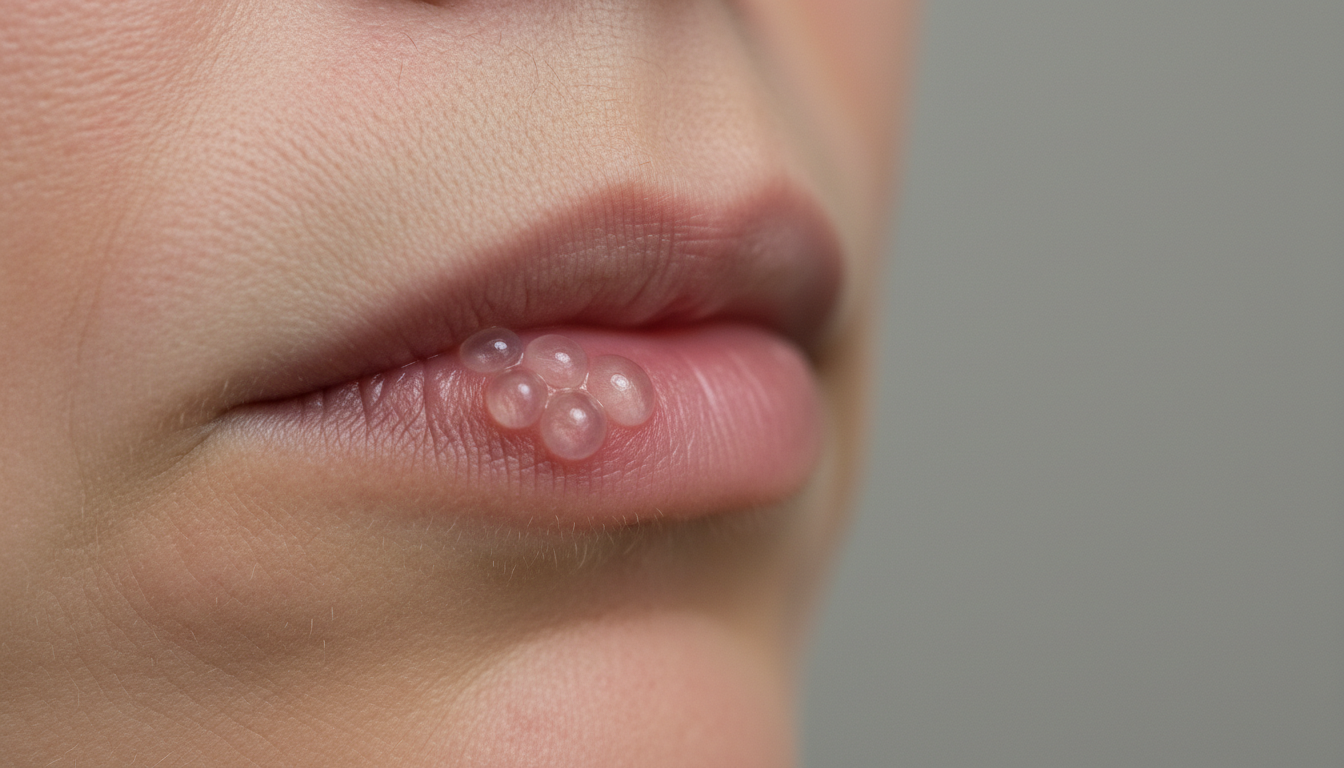
How herpes spreads, and how it does not
Herpes spreads through direct contact with infected skin or mucous membranes. The specific routes:
- Skin-to-skin contact during a visible outbreak (highest transmission risk per contact event)
- Skin-to-skin contact during asymptomatic viral shedding (lower per-contact risk but high cumulative risk over time)
- Saliva contact for HSV-1: kissing, shared lip balm, shared utensils, shared cigarettes, shared mouthpieces
- Vaginal, anal, and oral sexual contact for HSV-2 (and for HSV-1 reaching the genitals)
- Mother to baby during vaginal birth, particularly if the mother has a primary infection during the third trimester
Things that do not transmit herpes, despite frequent worry:
- Toilet seats. The virus dies quickly on hard surfaces.
- Towels, clothing, or bedding after an outbreak has cleared.
- Casual social contact: handshakes, hugs, sharing a room.
- Pools, hot tubs, or saunas.
- Tears or sweat in normal amounts.
The most important nuance is asymptomatic shedding. People with HSV-1 or HSV-2 can release infectious virus from the skin or mucous membranes on days when they feel completely fine and look completely normal. Genital-shedding studies summarized in the CDC STI Treatment Guidelines show HSV-2-positive adults release virus on a meaningful share of asymptomatic days. Most new herpes transmissions happen during these symptom-free shedding periods, not during visible outbreaks. This is why public-health framing has shifted away from "avoid sex during outbreaks" toward continuous risk reduction through suppressive antivirals, condoms, and partner testing.
If most herpes transmissions happen on days with no symptoms, then "I will just avoid sex when I have an outbreak" is an incomplete prevention strategy. Daily suppressive antivirals reduce viral shedding and, per the CDC STI Treatment Guidelines, substantially reduce transmission risk in serodiscordant couples (one partner HSV-positive, the other HSV-negative). Consistent condom use further reduces per-act risk. Partner testing matters for the same reason: a partner who has never had a noticeable outbreak can still be infected and shedding.
Recurrence and what triggers outbreaks
After the first infection, both viruses establish lifelong latency in nerve cells. They reactivate periodically, travel back down the nerve to the original site of infection, and cause an outbreak there. The triggers that prompt a reactivation are fairly consistent from person to person, and most people learn to recognize their own pattern over time.
Recurrence patterns differ by virus and by individual. Most people with genital HSV-2 have several outbreaks early on and gradually fewer over the years. The frequency of visible outbreaks tends to drop, and a meaningful minority stop having symptomatic recurrences entirely. The virus is still present and can still shed asymptomatically; it simply stops causing visible outbreaks.
Genital HSV-1 follows a similar but milder course: fewer early outbreaks and a faster decline in recurrence frequency. Oral HSV-1, the familiar cold sore, is highly variable. Some people get one or two cold sores a year, others get them monthly during stressful stretches, and some never have a recurrence after the initial childhood infection.
Common outbreak triggers
Most people identify two or three personal triggers within the first year of recognized outbreaks, and can soften recurrences by avoiding them or starting episodic antivirals at the first prodromal tingle.
- Physical stress: illness, fever, surgery, or sleep deprivation Common
- Emotional stress Common
- Hormonal changes, particularly around menstruation Common
- UV exposure, such as a sunny day at the beach Less common
- Local skin trauma: chapped lips, dental work, friction, or waxing Less common
- Immune suppression: HIV, chemotherapy, immunosuppressive drugs, or organ transplantation Rare
How herpes testing works
There are three main ways to diagnose herpes, and they answer different questions:
- Visual examination during a visible outbreak. A clinician looks at the lesion and can often make a presumptive diagnosis from its appearance and your history. This identifies an outbreak but does not reliably distinguish HSV-1 from HSV-2.
- PCR swab of an active lesion. A swab from the wet base of a fresh blister is sent to a laboratory for nucleic acid amplification testing. This is the most sensitive test during an outbreak and identifies the strain, but it only works while a sore is present, ideally before it crusts over.
- Blood antibody testing (type-specific IgG). This looks for antibodies your immune system has made against HSV-1 or HSV-2 glycoprotein G, a protein on the surface of the virus. Antibodies typically take 6 to 12 weeks to develop, with a small share of people taking up to 16 weeks. Blood testing is the only way to learn your status when you have no lesion to swab.
Our at-home herpes kits are blood antibody tests that use a fingerstick sample on a lateral-flow strip, the same chemistry as a home pregnancy test. You clean a fingertip, prick it with the included lancet, place a drop of blood on the sample well of the cassette, add the buffer fluid, and wait about 15 minutes. Test and control lines develop in the result window, indicating HSV-1 antibodies, HSV-2 antibodies, both, or neither. These are lateral-flow immunoassays rather than laboratory NAAT or PCR tests; the technologies complement each other but are not interchangeable.
Two performance terms matter when you read the result. Sensitivity is the share of truly infected people the test correctly flags as positive; higher sensitivity means fewer false negatives. Specificity is the share of uninfected people correctly cleared as negative; higher specificity means fewer false positives. The CDC STI Treatment Guidelines describe sensitivity for HSV-2 type-specific IgG antibody tests in the 80% to 98% range. Specificity is more variable: it depends on the assay and on the magnitude of the positive signal, known as the index value. One widely used commercial assay, the HerpeSelect HSV-2 EIA, has an overall specificity of about 57 percent, dropping to roughly 40 percent for borderline-positive index values in the 1.1 to 2.9 range, per real-world data cited in the CDC STI Treatment Guidelines.
That variability is why the home cassette is a screening tool, and why the CDC recommends a confirmatory test, often the Western blot at a reference laboratory, before anyone acts on a positive screening result. The CDC also does not recommend routine HSV antibody screening for adults without symptoms. At low pretest probability, false positives can outnumber true positives, so the home antibody test is most informative after a known exposure, a partner's diagnosis, or unexplained recurrent genital symptoms, rather than as a general health check. A positive blood antibody test also reflects past exposure cumulatively: it cannot tell you when you were infected or which body region (oral, genital, or both) the infection lives in.
HSV Antibody Seroconversion Window
- Week 0 Exposure
Virus transmits; no antibodies yet, so a blood test cannot detect it
- Week 3 Early window
Some people begin to seroconvert, but a negative result here is unreliable
- Week 12 Likely detectable
IgG antibodies are detectable in most people; the standard time to test
- Week 16 Outlier seroconverter
A small minority seroconvert this late; re-test if an earlier result was negative
Most people develop detectable IgG antibodies by 12 weeks; a small minority take up to 16.
Which test fits your situation, and when to test
The most common cause of a misleading result is testing too soon. Your immune system needs time to build detectable IgG antibodies after a new infection, so a blood test taken inside the window can read negative even when a real infection is present. If you have a known or suspected exposure date, the practical rule is to wait at least 12 weeks before a home antibody test, and to repeat at 16 weeks if the first result is negative and you remain concerned.
A home antibody test is a good fit when:
- You had a known or suspected exposure 12 or more weeks ago and want your antibody status without a clinic visit.
- A current or recent partner has been diagnosed with HSV-1 or HSV-2 and you want to know whether you have also been exposed.
- You have unexplained recurrent genital symptoms and want a baseline antibody result before talking through further testing with a clinician.
- You are starting a new relationship and both partners want a baseline status check. You can reach our at-home herpes test for that purpose.
It is not the right tool when you currently have a fresh genital sore, blister, or ulcer. The right test then is a clinician-administered swab PCR of the lesion, which detects the virus directly and does not depend on antibody seroconversion. We do not sell swab-based herpes PCR tests, so for an active lesion a clinic visit is the better next step. The same applies if your suspected exposure was less than 12 weeks ago, or if you have no symptoms and no specific reason to test, where per CDC guidance routine antibody screening is not recommended.
Use a PCR swab at a clinic if you have a visible blister or sore right now. It is the most sensitive option for an active outbreak and identifies the strain. See a clinician within the first day or two of the lesion appearing, before it crusts. We do not sell swab-based herpes PCR tests.
Use a blood antibody test if you have no visible lesion but are worried about a past exposure, or want a baseline before a new relationship. Wait at least 12 weeks (ideally 16) after the exposure you are concerned about. The at-home fingerstick kits we sell fall in this second category.
If you have an active lesion AND want your overall HSV status, do both: a clinic swab now for the lesion, and a blood antibody test in 12 to 16 weeks for the full picture.
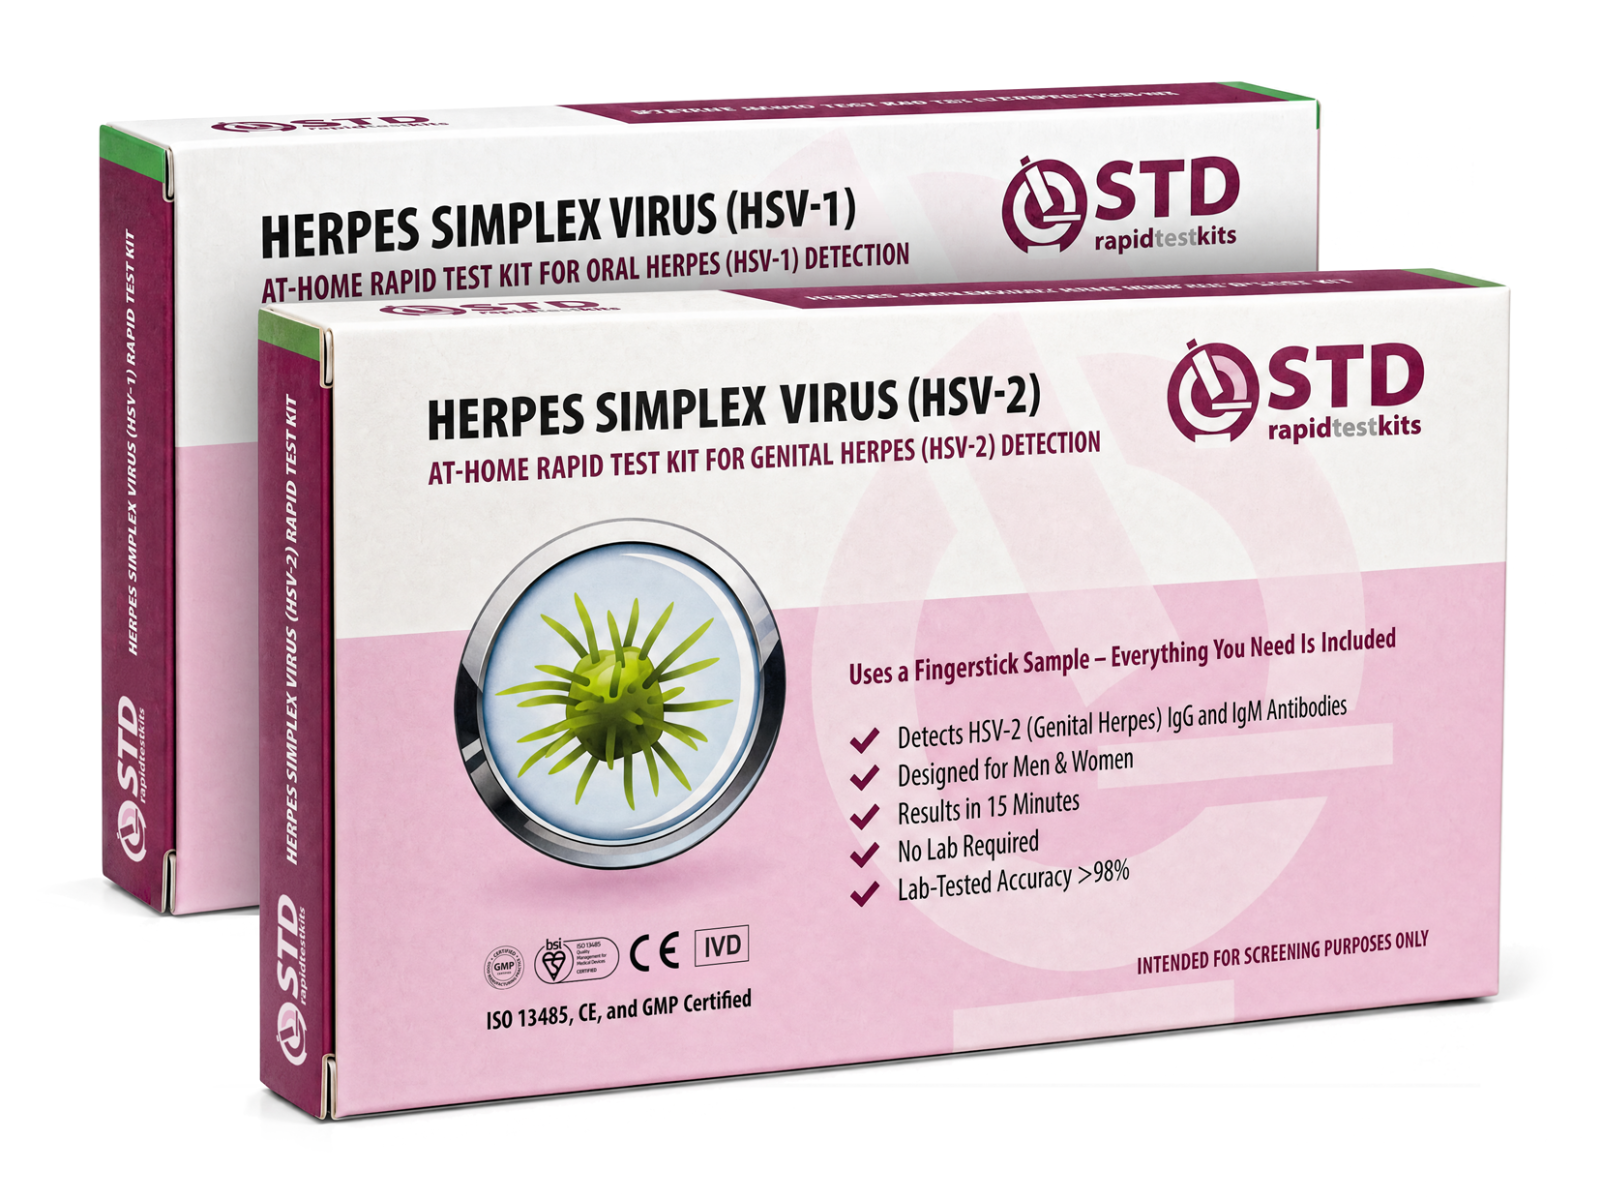
Reading your result without panic
The lateral-flow cassette will show a control line plus, depending on your antibody status, an HSV-1 line, an HSV-2 line, both, or neither. The control line confirms the test ran correctly. Without it, the result is invalid and you should repeat with a fresh cassette.
A negative result means no detectable IgG antibodies to the type tested. If at least 16 weeks have passed since your last possible exposure, this is generally informative. If less time has passed, plan a repeat test once you are past the window. A negative result does not tell you whether you may be exposed in the future or whether a different STI is present.
A positive result means IgG antibodies were detected, indicating past or current infection at some point. It does not tell you when the infection happened, whether the virus is currently active, or which body region (oral, genital, or both) the infection lives in. The next step is a confirmatory lab test through a clinician, particularly if you have no symptoms. Western blot at a reference lab remains the most specific confirmation method when a screening positive is questioned.
An invalid result (no control line, smudged window, or sample too small) means the test should be repeated. Common causes include not enough blood applied to the well, buffer skipped or measured incorrectly, or reading the cassette outside the timing window. Most kits ship with two cassettes for this reason.
Negative: no detectable antibodies. Reliable only if at least 16 weeks have passed since your last possible exposure. Otherwise repeat after the window closes.
Positive: antibodies detected. Confirm with a clinician-ordered lab test before drawing conclusions about timing, location, or treatment.
Invalid (no control line): the test did not run correctly. Repeat with a fresh cassette and follow the timing instructions carefully.
Privacy, cost, and the practical side
The appeal of home herpes testing is straightforward: privacy, no clinic appointment, a fast result, and a lower out-of-pocket cost than an uninsured clinic visit, with no insurance claim or explanation-of-benefits that a policyholder might later see. A rapid lateral-flow blood antibody test returns a result in about 15 minutes. A mail-in lab kit, a different category we do not sell, typically takes 2 to 5 business days, and clinic-based serology usually takes several days through to about a week.
Cost varies by kit. Single-infection HSV-1 or HSV-2 tests are usually the lowest-cost option, a combined HSV-1 plus HSV-2 panel costs slightly more, and combination kits that bundle HSV with HIV, syphilis, and other blood-based infections offer the best per-test value if you want a wider screen. For screening after the window period, a correctly used rapid lateral-flow test is comparable in accuracy to lab serology, with the important caveat that a reactive result should be confirmed by a clinician.
One trade-off is worth naming: home testing skips the clinical conversation that usually accompanies a positive result. If your test is positive, a follow-up with a clinician matters for confirmation and for discussing treatment and partner notification. If a home result is reactive, booking a clinician appointment for confirmation is the practical next step before any treatment or disclosure decisions.
Three testing paths compared
| Test path | Turnaround | Privacy | Positive needs confirmation? |
|---|---|---|---|
| Home rapid lateral-flow (sold here) | About 15 minutes | Result stays at home | Yes, lab test via a clinician |
| Mail-in lab kit (not sold here) | 2 to 5 business days | Sample handled by a third-party lab | Often built in, otherwise via clinician |
| Clinic blood serology | Several days to about a week | Captured in your medical record | Often run as part of the workup |
Home rapid testing is fastest and most private; clinic testing folds confirmation into the visit.
How to reduce herpes transmission risk
No behavior completely eliminates herpes transmission risk for someone who is sexually active with herpes-positive or untested partners. Several strategies meaningfully reduce it, and combining them works better than any single one:
- Daily suppressive antivirals for the herpes-positive partner. Per the CDC STI Treatment Guidelines, valacyclovir 500 mg once daily substantially reduces transmission to a susceptible partner in serodiscordant couples.
- Consistent condom use, which meaningfully reduces per-act HSV-2 transmission risk, with reduced effectiveness for areas a condom does not cover (the scrotum, the upper thighs, the perineum).
- Avoiding sex during outbreaks and prodromal symptoms, since per-act transmission risk is highest when lesions are visible or imminent.
- Disclosing status to partners so they can make informed decisions and consider antiviral suppression for themselves.
- Testing both partners before becoming sexually active, so each person knows their HSV status. This is most useful when starting a serious relationship.
Used together, suppressive antivirals plus condoms plus avoiding sex during outbreaks gives the strongest protection currently available short of abstaining, which is why clinicians often counsel stacking all three for serodiscordant couples planning long-term partnerships.
One related risk is worth naming: HSV-2 infection is associated with an increased risk of acquiring HIV through sexual exposure, per CDC and WHO surveillance. If you or a partner has HSV-2 and there is any concern about HIV exposure, add an HIV test to your plan rather than relying on the HSV result alone. For HSV-1 specifically, avoiding kissing during a visible cold sore prevents most transmission, and taking valacyclovir or acyclovir at the first prodromal tingle can shorten an outbreak by a day or two and reduce its peak severity.
Living with herpes and what comes after a positive
Herpes is not a serious medical condition for most adults. Outbreaks are uncomfortable, and stigma is real and outsized relative to the physical impact. For most healthy adults the day-to-day reality is mild: occasional outbreaks, manageable with antivirals if needed, and no effect on lifespan or fertility.
Antivirals do not cure HSV. Oral acyclovir, valacyclovir, and famciclovir suppress replication, shorten outbreaks, reduce recurrence frequency, and lower transmission risk to partners, but the virus stays in nerve tissue for life. Per the CDC STI Treatment Guidelines, valacyclovir 500 mg taken daily is the standard suppressive regimen, while episodic therapy taken at the first sign of an outbreak is an alternative when recurrences are infrequent.
Some situations need extra attention:
- Pregnancy. A new HSV infection during the third trimester is the highest-risk scenario for neonatal herpes, which is rare but serious. Discuss your status with your obstetric provider; many recommend suppressive therapy from week 36 onward in HSV-2-positive pregnancies, and a cesarean delivery if active lesions are present at the time of labor.
- Compromised immune systems. People with HIV, organ transplants, or active chemotherapy can have more severe and more frequent outbreaks, and long-term antiviral suppression is often used.
- First-time outbreaks can be severe enough to warrant a clinic visit for prescription antivirals; over-the-counter creams are not enough for a primary infection.
If a home antibody test comes back positive, the right follow-up is a clinician visit to confirm with a lab test, to discuss whether suppressive or episodic therapy fits your pattern, and to walk through partner notification. The NHS genital herpes guidance offers a similar treatment framework, and patient-facing summaries such as MedlinePlus can help, particularly for HSV-2 where stigma has historically been heavier.
Type-specific serologic tests can be useful for partners of persons who have genital herpes. Screening for HSV-1 or HSV-2 infection in the general population is not indicated.
Common myths worth correcting
Stigma drives a lot of misinformation about herpes, and a few beliefs come up again and again. One of the most stubborn is that only "certain types of people" get herpes. That is false. NHANES 2015 to 2016 surveillance data published by the National Center for Health Statistics found roughly 47.8 percent of US adults aged 14 to 49 carry HSV-1 and 11.9 percent carry HSV-2. Globally the WHO estimates HSV-1 prevalence at about 64 percent of people under age 50. It is among the most common viral infections in the world and does not track to any one demographic. The misconceptions below come up almost as often.
Five more herpes myths, corrected
Myth: You can only catch herpes from someone with visible sores.
Fact: Asymptomatic shedding accounts for most new transmissions. People with HSV-1 or HSV-2 can pass the virus on days when they feel and look completely normal, which is the central reason herpes is so widespread.
Myth: Cold sores are not herpes.
Fact: Cold sores are HSV-1 lesions, in the same family of viruses as genital herpes. The cultural split between them is not biologically meaningful; they are the same kind of infection in different anatomic locations.
Myth: You will know if you have herpes.
Fact: The majority of people with either virus never have a recognized outbreak. Symptoms get attributed to ingrown hairs, yeast, jock itch, or razor burn. A type-specific antibody test is the only reliable way to know your status when you have not had clear outbreaks.
Myth: Once you have had an outbreak, you can never have a healthy sex life.
Fact: Most herpes-positive people in long-term relationships do not transmit to their partners with reasonable precautions. With disclosure, suppressive antivirals when appropriate, and condom use, many serodiscordant couples stay serodiscordant for decades.
Myth: HSV-1 turns into HSV-2 over time.
Fact: HSV-1 and HSV-2 are two distinct viruses, and neither converts into the other. A person can be infected with one, the other, or both independently.
Your next step
What to do now depends on whether you have symptoms and how long it has been since a possible exposure. Use the quick guide below to find the right starting point, then confirm anything that needs confirming with a clinician.
What should I do next?
Do you have a fresh genital or oral sore, blister, or ulcer right now?
Yes: See a clinic for a PCR swab of the lesion before it crusts. That test detects the virus directly and identifies the strain. We do not sell swab-based PCR tests.
Was your last possible exposure at least 12 weeks ago, with no current sore?
Yes: An at-home blood antibody test is appropriate now and can identify HSV-1, HSV-2, or both.
Did a home antibody test come back positive?
Yes: Book a clinician appointment for confirmatory testing, often a Western blot, before making any treatment or disclosure decisions.
No: If the result was negative but your exposure was recent or you remain concerned, retest once you are past the 16-week mark.
Guidance only; a clinician can advise based on your specific situation.
Frequently asked questions
- How long after exposure can a herpes blood test detect infection?
- Wait at least 12 weeks after the suspected exposure for the most reliable result. IgG antibodies develop within 6 to 12 weeks for most people, with up to 16 weeks needed for a small minority. PCR swab testing of an active lesion has no window-period delay and can identify the strain immediately, but it only works during a visible outbreak and is administered at a clinic.
- How accurate are at-home herpes test kits?
- The variable that matters most is specificity, not sensitivity. Per the CDC STI Treatment Guidelines, HSV-2 type-specific IgG assays show sensitivity of 80% to 98%, but specificity drops sharply for borderline-positive results: the most widely used commercial assay falls to roughly 40 percent specificity at low index values, so a weak positive is often a false alarm. That is why any positive home result should be confirmed by a clinician-ordered Western blot, especially without symptoms. At-home lateral-flow kits use the same antibody-detection principle and perform most reliably 12 to 16 weeks after exposure.
- Can a home antibody test detect an active herpes outbreak?
- No. Home antibody tests detect your immune system's response to HSV, not the virus itself. The right test for an active genital or oral lesion is a clinician-administered swab PCR of the sore, which detects viral DNA directly. We do not sell swab-based herpes PCR tests; for an active outbreak, see a clinic within the first few days of the lesion appearing.
- If I test positive for HSV-1, do I have genital herpes?
- Not necessarily. A positive HSV-1 antibody test confirms exposure to the virus but does not tell you where it lives in your body. Most HSV-1 infections are oral and were acquired in childhood through non-sexual contact. A small but growing share of new genital herpes infections are caused by HSV-1 transmitted through oral sex. Site-specific diagnosis requires a PCR swab during an active lesion.
- Can I transmit herpes if I have no symptoms?
- Yes. In genital HSV-2 infection, most new transmissions happen on days with no visible symptom, through asymptomatic viral shedding. Daily suppressive antiviral therapy reduces that shedding and, per the CDC STI Treatment Guidelines, substantially lowers transmission risk in serodiscordant couples.
- Should I test for HSV if I have no symptoms and no known exposure?
- The CDC does not recommend routine HSV antibody screening for asymptomatic adults without a specific reason. At low pretest probability, false positives can outnumber true positives, which can cause distress without changing what you would actually do. Home tests are most informative when there is a specific reason to use one: a known exposure, a partner's diagnosis, recurrent unexplained genital symptoms, or a baseline check before a new relationship.
- Is there a cure for herpes?
- No. Once acquired, HSV-1 and HSV-2 establish lifelong latency in nerve cells and cannot be cleared by current medications. Antivirals such as acyclovir, valacyclovir, and famciclovir suppress replication; they shorten outbreaks, reduce frequency, and reduce transmission risk, but they do not eliminate the virus. Vaccine and therapeutic research is ongoing, but no cure is currently available.
- Are home herpes tests confidential?
- When you buy a true at-home rapid lateral-flow kit, the result stays with you. There is no lab transmission, no insurance claim, and no medical record entry unless you choose to share the result with a provider. Mail-in lab kits, a different category, do involve a third-party lab; review that company's privacy policy if you go that route.
- World Health Organization. Herpes simplex virus fact sheet, including global prevalence estimates for HSV-1 (about 3.8 billion people under 50) and HSV-2 (about 520 million aged 15 to 49) and the clinical course of infection.
- US Centers for Disease Control and Prevention. Herpes information page covering symptoms, transmission, testing, and treatment, source for the statement that most people with genital herpes have no symptoms or symptoms so mild they go unnoticed.
- US Centers for Disease Control and Prevention. STI Treatment Guidelines, Genital Herpes. Window-period guidance, the 80% to 98% sensitivity range, the HerpeSelect HSV-2 EIA overall specificity (about 57 percent) and lower specificity at low-positive index values (about 40 percent at index 1.1 to 2.9), the recommendation against routine asymptomatic screening, Western blot confirmation guidance, the recurrence-frequency comparison, and the valacyclovir 500 mg suppressive regimen that reduces transmission in serodiscordant couples.
- National Center for Health Statistics. Prevalence of Herpes Simplex Virus Type 1 and Type 2 in Persons Aged 14 to 49: United States, 2015 to 2016. NCHS Data Brief No. 304. Source for the 47.8 percent HSV-1 and 11.9 percent HSV-2 US seroprevalence figures.
- NHS. Genital herpes overview, symptoms, and treatment guidance for the UK general public.
- MedlinePlus, US National Library of Medicine. Genital herpes patient information page, a plain-language summary of clinical features, testing, and treatment.
